
Senior Care Means Ongoing Medical Management, Not Home Help
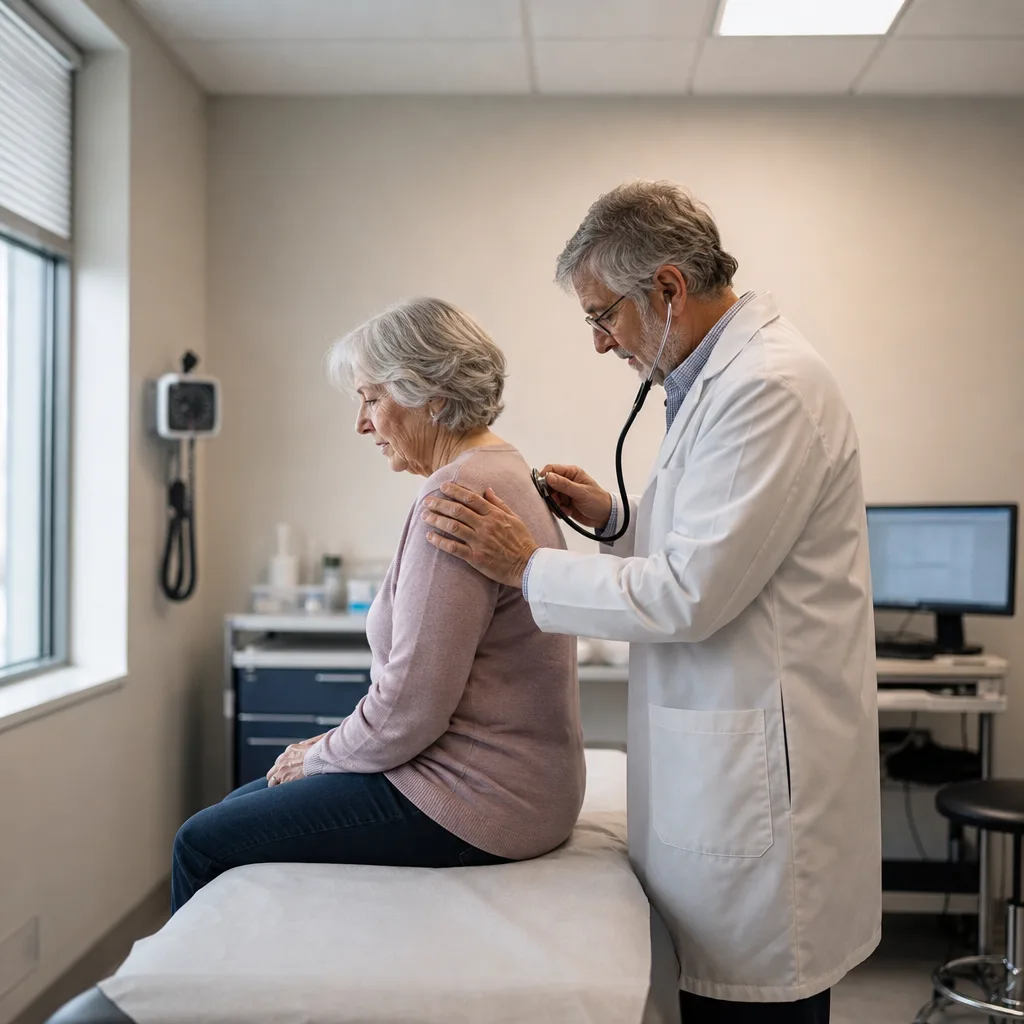
Senior care in a medical sense means a doctor managing your health conditions, medications, and screenings over time. It's not housekeeping, bathing help, or a ride to the store. Those are real needs, but they're a different service, and knowing the difference saves families weeks of calling the wrong places.
When people search for senior care, they usually mean one of two very different things. One is help around the house. Someone to cook, clean, help with a shower, drive to the grocery store. The other is medical. A physician who knows the whole health picture and manages it month after month. Both matter. They're not the same job, and they're not done by the same people.
What we do is the medical side. That means looking after the conditions that tend to stack up with age and making sure they aren't quietly working against each other. Blood pressure. Cholesterol. Diabetes. Thyroid disease. Arthritis. Asthma. Each one on its own is manageable. Four of them at once, with a different specialist prescribing for each, is where things get messy.
Here's the part that surprises families. Most of the trouble we're watching for isn't a new disease. It's the interaction between things already being treated. A blood pressure medication that works fine alone can leave someone lightheaded when a second one gets added after a stay in the hospital. A thyroid dose that was right five years ago may not be right now. Nobody is doing anything wrong. It's just that no single specialist is looking at the full list.
Ongoing medical senior care usually covers work like this:
- Chronic disease management for conditions like high blood pressure, diabetes, high cholesterol, and thyroid disorders
- Medication management and medication reconciliation, so the full list is reviewed together instead of one prescription at a time
- Annual wellness exams and preventive screenings appropriate for age and risk
- Lab testing and blood work to track how treatment is working, not just how it should be working
- Care coordination and specialist referrals, with someone keeping track of what each specialist recommended
- Transitional care and hospital care support after a stay in the hospital or a procedure
- Mental health support, including depression and anxiety, which often get missed in older adults
Notice what isn't on that list. No bathing assistance. No meal prep. No overnight sitting. If that's what your family needs right now, a home care agency is the right call, and you should make it. Plenty of people end up needing both, and that's fine. They just come from two different places.
The reason we cap our practice at 200 patients is directly tied to this. Managing six conditions, nine medications, and three specialists for one person takes real time. You can't do it well in a twelve-minute visit, and you can't do it well for three thousand patients. A small panel is what makes the ongoing part possible.
Chronic Conditions That Call for Consistent Senior Care
Some conditions can be treated once and left alone. Most of the ones that show up after 65 can't. They shift. A number that looked fine in March drifts by November, and nobody notices because nobody's comparing the two. That's the real argument for steady care instead of appointments booked only when something feels wrong.
High blood pressure is the clearest example. It doesn't hurt. There's no symptom telling you it climbed. The only way to know is to check it over and over, in the same way, and watch the line. The same goes for cholesterol and thyroid function. You're not treating a feeling. You're treating a trend.
Diabetes behaves differently but needs the same attention. Appetite changes with age. So does kidney function. A dose of medication that keeps blood sugar steady at 68 can start pushing it too low at 76. Low blood sugar in an older adult can look like confusion or a fall rather than the shakiness a younger person would feel. That's a case where the medication is working exactly as written and still causing harm.
Here's what consistent management tends to keep an eye on:
- High blood pressure, including whether it drops too far when standing up
- Diabetes, with attention to lows as well as highs
- High cholesterol and how it fits the whole cardiovascular picture rather than one number
- Thyroid disorders, where symptoms get written off as normal aging
- Asthma and breathing changes, which behave differently at Colorado altitude than at sea level
- Arthritis and the pain medications used for it, since those interact with a lot
- Depression and anxiety, which often look like fatigue, poor sleep, or loss of appetite in older adults
That last one deserves more weight than it usually gets. According to the National Institute of Health, depression in an older adult frequently doesn't sound like sadness.[1] It sounds like not wanting to go out anymore, or sleeping oddly, or losing interest in food. Families read it as slowing down. It's treatable, and it responds better when someone who knows the person's baseline notices the change.
Living along the Front Range adds two wrinkles. Greenwood Village sits above 5,000 feet, and thinner air is harder on people managing heart and lung conditions, especially anyone who moved here later in life. Winter is the other one. When ice makes sidewalks and driveways unsafe, walking drops off. Activity falls, and blood sugar and blood pressure both respond to that by spring. Knowing a patient's seasonal pattern is part of managing them well.
None of this requires anything dramatic. It requires someone reviewing the same conditions and the same medication list on a regular schedule, with enough history to tell the difference between a bad day and a real change. Keeping our panel at 200 patients is what makes that kind of memory possible.
Why a Smaller Patient Panel Changes the Senior Care Experience

Everything in the last two sections depends on one thing: time. Reviewing nine medications against six conditions isn't hard medicine. It's slow medicine. It takes a doctor who can sit with the list, ask what you took this week versus what's written on the bottle, and then remember that conversation six months later. Our practice is capped at 200 patients for that reason alone.
Think about what a standard visit asks of you. You've got fifteen minutes. You're supposed to cover the cardiologist's new prescription, the dizziness that started in October, your sleep, your mood, and last month's lab results. Most people pick two of those and drive home thinking about the other three. Older adults with several conditions are the ones this hurts most, because their list is the longest.
Here's what changes when the panel is small. Dr. Grenardo isn't meeting your health history for the first time each visit. He knows your baseline. He knows you walk the dog every morning until the ice comes, and that when you stopped doing it in January, something was different. That kind of knowing isn't a personality trait. It's what a limited panel buys you.
The direct access piece matters just as much for seniors. You can reach your physician by phone, text, or secure message. For an older adult, a question that gets answered the same day often prevents the thing that would have turned into an emergency room visit three days later. A new medication causing lightheadedness is a five-minute conversation. Left alone until the next available appointment, it's a fall:
- Unhurried annual wellness exams, with enough time to go through every condition and every medication rather than the top two
- Direct physician access by phone, text, and secure communication, so small concerns get handled before they grow
- Care coordination and specialist referrals, with one physician tracking what each specialist recommended and whether the pieces fit together
- Transitional care and medication reconciliation after a stay in the hospital, when the medication list changes most and errors happen most
- House call visits and telehealth visits, for the weeks when getting to an office isn't realistic
- Continuity, so the person reviewing your labs is the same person who reviewed them last year
Dr. Grenardo spent more than 30 years in clinical and executive healthcare, including time as Chief Medical Officer at Centura Health and Medical Director of its Clinically Integrated Network. He's seen from the inside why care fragments between specialists, hospitals, and primary care. OG Health is built to close that gap for a small number of people rather than to manage it at scale.
None of this is magic. It's a doctor with fewer patients, more time, and the same face across every visit. For an older adult with several conditions and a medication list that keeps changing, that turns out to be most of what good care is.
Care Coordination After a Hospital Stay or Specialist Visit
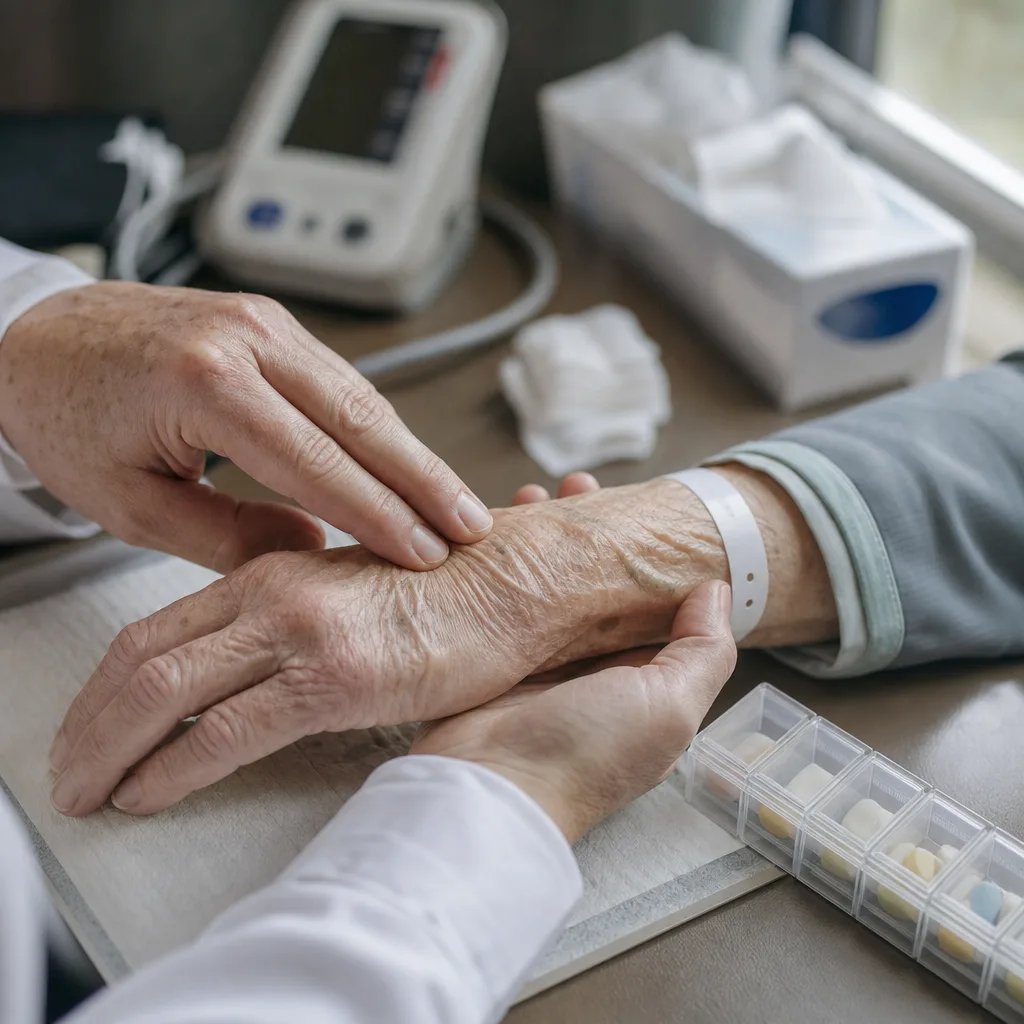
The riskiest week for an older adult usually isn't the week in the hospital. It's the week after. You come home with a discharge packet, two new prescriptions, one medication that was stopped, another whose dose changed, and instructions to follow up with somebody in ten days. Nobody sits down with you and compares that new list against what's already in your cabinet.
That gap is where the damage happens. A patient keeps taking the old blood pressure pill because nobody told them to stop, and now they're on two drugs doing the same job. A blood thinner gets started in the hospital and the arthritis medication at home quietly makes it riskier. Neither the hospital team nor the specialist can see the full cabinet. Only the physician who's been managing the whole picture can.
Specialist visits create smaller versions of the same problem. A cardiologist adjusts one thing. An endocrinologist adjusts another. Each decision is correct on its own. Put side by side, they can pull in opposite directions, and the person feeling the result is the patient wondering why they've been dizzy since Thursday.
Here's what coordination after a hospital stay or specialist appointment involves:
- Medication reconciliation, where the discharge list is compared line by line against what was being taken before, including anything stopped or changed
- Checking new prescriptions against existing conditions, not just against each other
- Reading what the specialist recommended, rather than relying on a patient's memory of a rushed appointment
- Deciding which follow-up labs or blood work are needed and when, so a new dose gets checked instead of assumed
- Watching for the symptoms that show up first after a change: lightheadedness on standing, confusion, poor appetite, new fatigue
- Telehealth visits or house call visits during the stretch when driving to an office isn't realistic
Timing matters more than families expect. The first two weeks home are when a medication error is most likely and when someone is least able to catch it themselves. If a dose changes, a fast check-in beats waiting for the scheduled follow-up. That's the difference between a phone call and a return trip to the emergency room.
Colorado adds one more thing worth naming. If a hospital stay lands in January or February, recovery happens during the weeks when icy driveways keep people indoors. Strength drops off fast at that age, and a patient who was walking daily before admission may not get back to it without someone asking. Discharge paperwork won't mention that. A physician who knows what your winters look like will.
Care coordination isn't paperwork. It's one doctor holding the whole list and being willing to say that two correct decisions, made separately, don't add up to a good plan.
When Senior Care Isn't the Right Fit Yet
Not everyone over 65 needs this. Plenty of older adults are on one medication, see their doctor once a year, and have no reason to change a thing. If that's you, keep doing what's working. Age by itself isn't a medical problem.
There are a few situations where we'd tell you straight out that we're not the answer, at least not today:
- What you need is help at home. Bathing, dressing, meals, laundry, rides to appointments. That's a home care agency, and no amount of physician time replaces it.
- Someone needs supervision around the clock. If a parent can't be left alone safely, the decision in front of you is about living arrangements, not about primary care.
- You're in an emergency right now. Chest pain, trouble breathing, sudden weakness on one side, a bad fall, sudden confusion. Call 911. Don't call an office and wait for a return message.
- You already have a primary care doctor you trust who knows your history and returns your calls. Continuity is the thing that matters most, and you already have it. Switching doctors restarts a relationship that's already built.
- The hard part is money, not medicine. If paying for prescriptions or transportation is the actual barrier, a care manager, a county aging office, or a social worker will do more for you than another doctor will.
That fourth one deserves a little more honesty. Families sometimes want to move a parent to a new doctor because the current office feels slow or impersonal. Sometimes that's the right call. But a doctor who's known someone for fifteen years carries information that doesn't transfer in a records request. They remember what a normal blood pressure looks like for that person, which medication caused trouble back in 2016, how this patient acts when something's wrong. Before you move, it's worth asking whether the real problem is the doctor or the fifteen-minute visit.
Timing matters too. If your father's health is stable and nothing has changed in two years, there's no urgency. The moment worth paying attention to is when the picture starts shifting. A new diagnosis. A hospital stay. A third specialist was added to the list. A medication count that climbed past five or six. A fall. Those are the points where fragmented care starts costing something real.
We also don't replace specialists. If someone needs a cardiologist, an oncologist, or a surgeon, they need that person. What we do is keep track of what all of them decided and make sure the pieces fit together. If your parent's care is genuinely well coordinated already, you don't need a second set of eyes on it.
Where this fits best is the person with several conditions, a medication list that keeps changing, and more than one doctor writing prescriptions. If that describes your situation and nobody is holding the whole picture, that's worth a conversation. If it doesn't, we'd rather you spend your time on the thing that helps.
Frequently Asked Questions
How is senior care different from a regular primary care doctor?
The difference is time and panel size, not the type of doctor. A regular primary care visit is often 15 minutes to cover everything, which is hard when someone has several conditions and a long medication list. A practice with a smaller patient panel can spend an unhurried visit going through every condition and medication instead of just the top two concerns.
Can this type of senior care work alongside my parent's specialists?
Yes, that's the main point of it. This service doesn't replace a cardiologist, oncologist, or surgeon your parents already see. Instead, one physician tracks what each specialist recommends and checks that the decisions fit together, since a cardiologist and an endocrinologist can each make a correct call that conflicts with the other.
What should I do if my parent seem dizzy or confused after a hospital stay?
Call your doctor right away instead of waiting for the scheduled follow-up. The first two weeks home are when a medication error is most likely, and dizziness or confusion can signal that a new prescription or dose change is causing trouble. A fast check-in at that stage can prevent a return trip to the emergency room.